

Six investigational therapies targeting hereditary haemorrhagic telangiectasia could transform treatment for a condition that remains without a single approved drug.
A wave of targeted therapies could transform the management of hereditary haemorrhagic telangiectasia (HHT), with six investigational drugs advancing through development for one of the world’s most common inherited bleeding disorders.
A new review published in The Lancet Haematology has highlighted the emergence of disease-specific treatments that could reduce chronic bleeding, improve anaemia and potentially reverse the vascular abnormalities underlying the condition.
HHT affects approximately one in 4000 to 5000 people worldwide, making it more than twice as prevalent as haemophilia. Despite its substantial disease burden, no therapies have been specifically licensed for HHT anywhere in the world.
“For every man with haemophilia, there is at least one woman and one man with hereditary haemorrhagic telangiectasia,” wrote the paper’s author Dr Hanny Al-Samkari, a haematologist and clinical investigator at the Massachusetts General Hospital and Harvard Medical School.
“The disease burden of hereditary haemorrhagic telangiectasia is substantial: three-quarters of patients develop progressive, moderate-to-severe chronic mucosal bleeding (i.e., epistaxis, gastrointestinal bleeding, heavy menstrual bleeding) due to numerous mucosal telangiectasias and arteriovenous malformations, resulting in iron deficiency anaemia in most patients.
“Intravenous iron and red cell transfusion requirements are common, and the magnitude of these requirements greatly eclipses that of other bleeding disorders.”
He said advances in understanding the molecular mechanisms driving HHT had opened the door to a new generation of treatments.
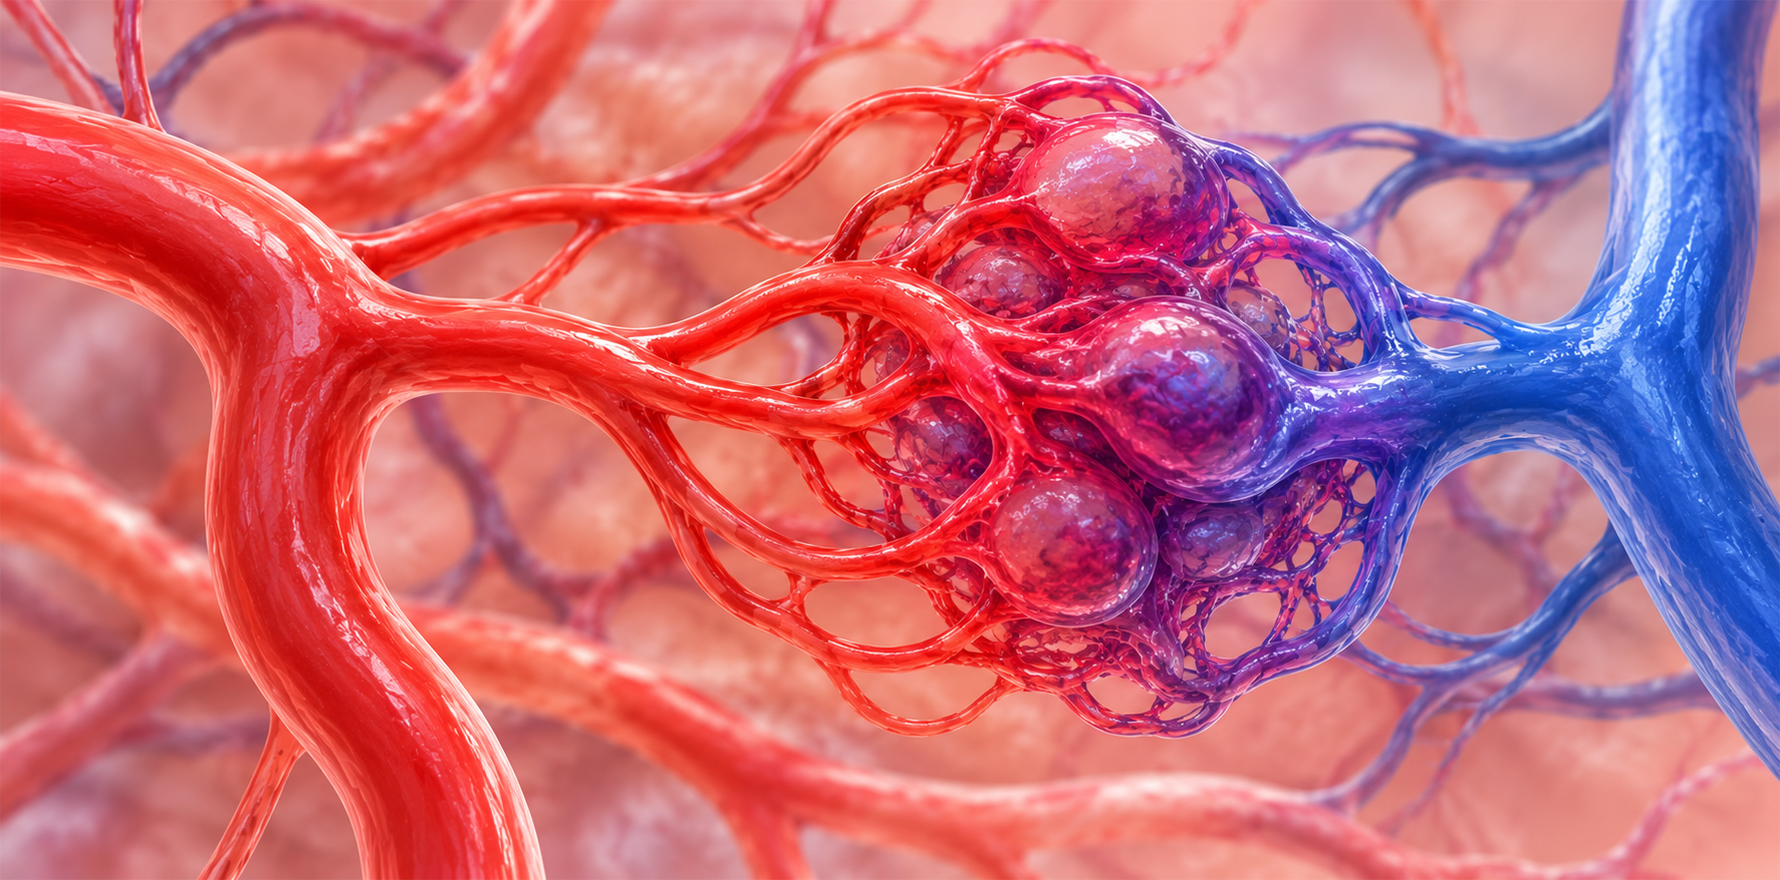
HHT is an autosomal dominant vascular disorder characterised by abnormal angiogenic signalling, resulting in fragile telangiectasias and arteriovenous malformations (AVMs).
Approximately three-quarters of patients develop progressive moderate-to-severe mucosal bleeding, including recurrent epistaxis and gastrointestinal bleeding, frequently resulting in iron deficiency anaemia and dependence on intravenous iron or red blood cell transfusions.
The condition also carries substantial risks beyond bleeding, with approximately one in 30 patients experiencing intracranial haemorrhage and up to one in six developing venous or arterial thromboembolism.
Current treatments rely largely on repurposed antifibrinolytic and antiangiogenic agents, which have shown variable efficacy, substantial toxicities, and frequent loss of response.
However, six novel agents targeting distinct vascular and haemostatic pathways are now in development, potentially offering more effective and better-tolerated options.
Among the most advanced is engasertib, an oral selective AKT1/AKT2 inhibitor designed to suppress the excessive angiogenic signalling responsible for abnormal blood vessel formation in HHT.
In a phase 1b randomised, placebo-controlled trial involving 75 adults with moderate-to-severe bleeding, engasertib produced dose-dependent improvements in epistaxis frequency, duration, and intensity.
During an open-label extension, mean epistaxis frequency and duration improved by 55% and 66%, respectively, relative to baseline at 12 months.
The drug was generally well tolerated, although rash, diarrhoea, and hyperglycaemia were reported more frequently than with placebo.
The findings have prompted the global phase 3 HEROIC trial, which will enrol 240 adults with HHT and moderate-to-severe bleeding to evaluate engasertib 40mg daily against placebo.
The primary endpoint is change in epistaxis frequency, with secondary measures including bleeding severity, haematological impact, and quality of life.
Two additional oral agents, ATV-1601 and TER-4480, selectively inhibit AKT1 rather than both AKT1 and AKT2.
This approach could potentially preserve the therapeutic effects of AKT inhibition while reducing adverse events such as hyperglycaemia, which is thought to be mediated predominantly by AKT2 inhibition, Dr Al-Samkari wrote.
The international Harmony-HHT trial is evaluating ATV-1601 in 100 adults with moderate-to-severe bleeding, while an initial proof-of-concept trial of TER-4480 is expected to begin in 2027.
Dr Al-Samkari said another promising approach involves ALN-6400, an investigational small interfering RNA therapy designed to reduce circulating plasminogen and produce sustained antifibrinolytic activity.
Administered subcutaneously once every three months, ALN-6400 could offer an alternative to oral antifibrinolytics such as tranexamic acid, which require frequent dosing and have demonstrated only modest efficacy in HHT.
The international phase 1/2 InsigHHT trial, which includes Australian sites, is evaluating the safety and efficacy of ALN-6400 in patients with moderate-to-severe bleeding.
The study will assess epistaxis severity, haemoglobin levels, haematological support requirements, and quality of life.
Although plasminogen reduction raises theoretical concerns about thromboembolic risk, the review noted that evidence from preclinical studies, genetic analyses, and experience with antifibrinolytic therapies had not demonstrated an increased risk, Dr Al-Samkari said.
Nevertheless, establishing the long-term safety of sustained plasminogen suppression will be important, particularly given the underlying thromboembolic risk associated with HHT.
Other investigational therapies aim to address the vascular abnormalities more directly.
DIAG723, a bispecific antibody administered subcutaneously every two weeks, is designed to restore deficient ALK1–BMPRII signalling, a central molecular defect in HHT.
Preclinical studies have demonstrated reversal of AVMs in multiple mouse models, along with improvements in haemoglobin and survival.
Related

The ongoing phase 1/2 DIAMOND trial will assess safety and efficacy, including changes in bleeding and imaging evidence of AVM regression.
A further candidate, TX2100, targets the apelin receptor, which is involved in abnormal endothelial proliferation and angiogenesis.
By selectively blocking this pathway, researchers hope to achieve antiangiogenic effects with fewer systemic toxicities than existing VEGF-targeted treatments.
Early clinical development is underway, with HHT-specific trials expected to commence in late 2026.
Dr Al-Samkari said the emergence of multiple therapies with different mechanisms of action was particularly important given the heterogeneity and progressive nature of HHT.
The review distinguishes between treatments that primarily improve haemostasis and those that directly target abnormal vascular signalling.
While both approaches could reduce bleeding, vascular-directed treatments might also prevent the development or progression of AVMs, or potentially reverse existing lesions.
However, evidence of clinical AVM regression in humans remains limited, and the longer-term benefits and safety of the investigational agents are yet to be established.
For haematologists, Dr Al-Samkari said the developments could mark a significant shift from managing recurrent bleeding and its consequences towards modifying the underlying disease process.
The review also highlighted the need for treatments that reduce dependence on intravenous iron and blood transfusions, while improving patient-reported outcomes and quality of life.
Dr Al-Samkari said the rapid expansion of the therapeutic pipeline reflected a long-overdue recognition of the burden imposed by HHT.
“Since it was first recognised as a distinct disease from haemophilia by the French physician Henri Jules Louis Marie Rendu in 1896, hereditary haemorrhagic telangiectasia has been a largely neglected inherited bleeding disorder,” he wrote.
“With modern recognition of the relatively high prevalence and costs of hereditary haemorrhagic telangiectasia, major advances in the foundational science of hereditary haemorrhagic telangiectasia pathophysiology, published high-quality prospective registry data describing the striking and severe burden of disease, and overdue investment in therapeutic development by industry, that is now changing.
“Each of the agents covered in this article has potential unique benefits and potential agent-specific limitations.
“Given the heterogeneity of hereditary haemorrhagic telangiectasia (evident clinically and yet to be unlocked at the biomarker level), progressive nature, and numerous bleeding and non-bleeding manifestations of hereditary haemorrhagic telangiectasia, there can be no doubts that an armamentarium of safe, effective therapeutics with unique mechanisms of action are required to adequately treat this disease.
“With the ongoing development of the novel agents described herein, we are finally on the road to achieving this goal, to the ultimate benefit of more than 1.6 million individuals worldwide with this morbid bleeding disorder.”
